The ICD 10 code for stroke depends on the stroke type and the care setting. Most ischemic strokes with no extra detail use I63.9. However, bleeding strokes, old strokes, and lasting deficits each use different codes. So one quick lookup rarely settles the claim.
Stroke claims carry high payment risk. Payers review them closely because they affect hospital payment and patient risk scores. A small coding slip can trigger a denial or an audit.
This guide explains each code family in plain terms. You will also see real examples, billing steps, and common errors.
ICD 10 Code for Stroke at a Glance
Most readers want the answer first. So here is the quick map. Each row still needs detail from the provider’s note.
| Situation | Code | Meaning |
| Stroke or CVA, no detail | I63.9 | Cerebral infarction, unspecified |
| Lacunar infarction | I63.81 | Other cerebral infarction due to small artery occlusion |
| Bleeding inside the brain | I61.- | Nontraumatic intracerebral hemorrhage |
| Bleeding around the brain | I60.- | Nontraumatic subarachnoid hemorrhage |
| Old stroke, no deficits | Z86.73 | Personal history of TIA and cerebral infarction without residual deficits |
| Stroke with lasting deficits | I69.- | Sequelae of cerebrovascular disease |
What Is the ICD-10 Code for Stroke?
The ICD 10 code for stroke is I63.9 when the note says only “stroke” or “CVA.” The index sends both terms to cerebral infarction, unspecified. Therefore, I63.9 serves as the default for stroke not otherwise specified.
Coders also search cva icd 10 and cerebrovascular accident icd 10. Both terms mean the same thing in the index. So the answer stays I63.9 unless the note adds a cause or location. A search for ICD 10 code for stroke leads to the same place.
However, I63.9 is a fallback. If the provider names a cause, use a more specific code. Payers prefer detail, and I63.9 gives them very little.
Cerebral Infarction ICD 10 Code Basics
Ischemic stroke means a blocked vessel starves part of the brain. ICD-10-CM calls this cerebral infarction. The cerebral infarction ICD 10 code family is I63. The category itself is a header, so you must pick a child code.
The I63 codes follow the cause and the artery involved.
| Code Range | Meaning |
| I63.0- | Thrombosis of precerebral arteries |
| I63.1- | Embolism of precerebral arteries |
| I63.2- | Unspecified occlusion or stenosis of precerebral arteries |
| I63.3- | Thrombosis of cerebral arteries |
| I63.4- | Embolism of cerebral arteries |
| I63.5- | Unspecified occlusion or stenosis of cerebral arteries |
| I63.6 | Cerebral venous thrombosis, nonpyogenic |
| I63.8- | Other cerebral infarction, including I63.81 and I63.89 |
| I63.9 | Cerebral infarction, unspecified |
Precerebral arteries include the carotid and vertebral arteries. Cerebral arteries sit inside the skull. Many codes also add the side. For example, I63.411 means embolism of the right middle cerebral artery. I63.412 means the left side.
What Is the ICD 10 Code for Ischemic Stroke?
Ischemic stroke has no single code. The ICD 10 code for ischemic stroke comes from the I63 family. The cause, artery, and side decide the final pick. If the note gives none of these, I63.9 applies.
What Is the Primary ICD-10 Code for an Acute Ischemic Stroke?
The icd 10 code for acute stroke is the most specific I63 code the note supports. So the primary code is not one fixed value. Acute cerebral infarction ICD 10 coding follows the same rule. Use I63.9 only when no detail exists.
Here is a real example. A 68-year-old man arrives with sudden right-sided weakness and slurred speech. Imaging shows a clot blocking the left middle cerebral artery. The provider documents an embolic infarct. The coder reports I63.412, which names embolism of the left middle cerebral artery.
Lacunar Infarction ICD 10 Code
Lacunar infarction ICD 10 coding uses I63.81. The index entry reads Infarction, cerebral, lacunar. The code title is “Other cerebral infarction due to occlusion or stenosis of small artery.” ICD-10-CM added this code in 2019.
Providers use the term when small deep vessels cause the stroke. So the note should say “lacunar” clearly. Otherwise, the coder may fall back to I63.89 or I63.9.
Detailed ICD-10 Codes for Different Types of Hemorrhagic Stroke
Hemorrhagic strokes involve bleeding, not a blockage. The hemorrhagic stroke ICD 10 code depends on where the blood collects. These codes sit in I60 through I62. Traumatic bleeds use S06 injury codes instead.
Subarachnoid Hemorrhage (I60)
This bleed occurs in the space around the brain. The code follows the source artery.
| Code | Source of Bleeding |
| I60.0- | Carotid siphon and bifurcation |
| I60.1- | Middle cerebral artery |
| I60.2 | Anterior communicating artery |
| I60.3- | Posterior communicating artery |
| I60.4 | Basilar artery |
| I60.5- | Vertebral artery |
| I60.6 | Other intracranial arteries |
| I60.7 | Unspecified intracranial artery |
| I60.8 | Other subarachnoid hemorrhage |
| I60.9 | Subarachnoid hemorrhage, unspecified |
Intracerebral Hemorrhage (I61)
This bleed occurs inside the brain tissue. The code follows the location.
| Code | Location |
| I61.0 | Hemisphere, subcortical |
| I61.1 | Hemisphere, cortical |
| I61.2 | Hemisphere, unspecified |
| I61.3 | Brain stem |
| I61.4 | Cerebellum |
| I61.5 | Intraventricular |
| I61.6 | Multiple localized sites |
| I61.8 | Other intracerebral hemorrhage |
| I61.9 | Intracerebral hemorrhage, unspecified |
Other Nontraumatic Intracranial Hemorrhage (I62)
This group covers bleeding outside the brain tissue. Subdural bleeds use I62.0-, with fifth characters for acute (I62.01), subacute (I62.02), and chronic (I62.03). Extradural bleeds use I62.1. Unspecified intracranial bleeding uses I62.9.
Consider a patient with a bleed in the brain stem. The provider documents “intracerebral hemorrhage of the pons.” The coder reports I61.3. This choice is more precise than I61.9, so it supports the claim better.
What Are the Most Common ICD 10 Codes for Different Types of Stroke?
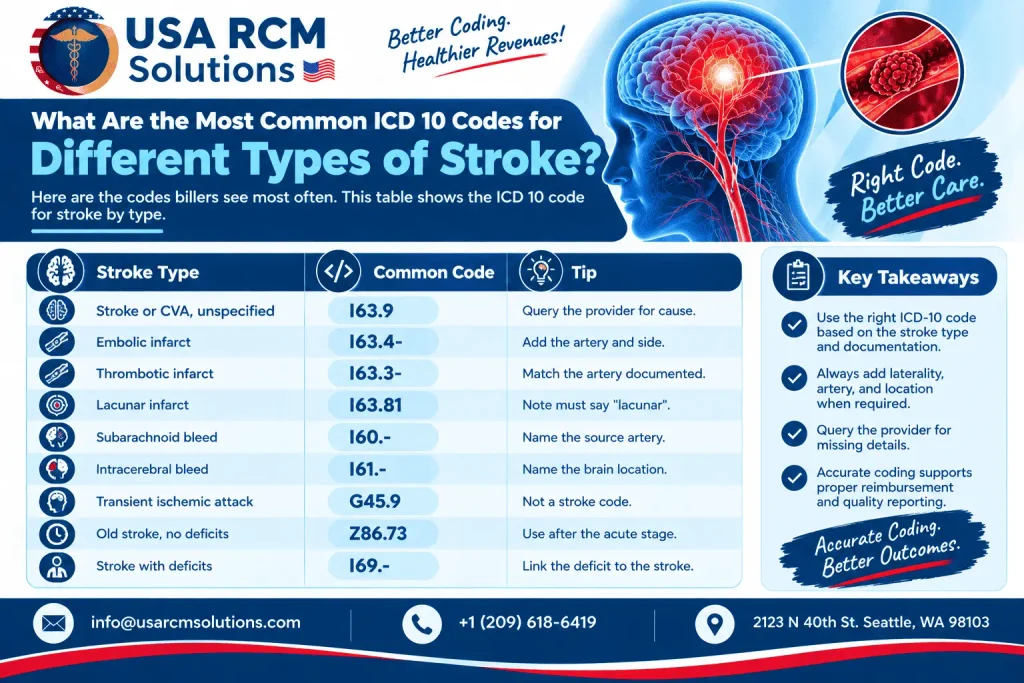
Here are the codes billers see most often. This table shows the icd 10 code for stroke by type.
| Stroke Type | Common Code | Tip |
| Stroke or CVA, unspecified | I63.9 | Query the provider for cause |
| Embolic infarct | I63.4- | Add the artery and side |
| Thrombotic infarct | I63.3- | Match the artery documented |
| Lacunar infarct | I63.81 | Note must say “lacunar” |
| Subarachnoid bleed | I60.- | Name the source artery |
| Intracerebral bleed | I61.- | Name the brain location |
| Transient ischemic attack | G45.9 | Not a stroke code |
| Old stroke, no deficits | Z86.73 | Use after the acute stage |
| Stroke with deficits | I69.- | Link the deficit to the stroke |
What Is the ICD-10 Code for Potential Stroke?
No code says “potential stroke.” The right choice depends on the care setting. This is where many outpatient claims go wrong.
In an outpatient setting, coders cannot report uncertain diagnoses. Words like “possible,” “probable,” and “rule out” do not count. Therefore, coders report the symptoms instead. Examples include R29.810 for facial weakness and R47.01 for aphasia. Providers use G45.9 when they diagnose a transient ischemic attack.
In an inpatient setting, the rule differs. A diagnosis documented as “probable” at discharge can be coded as if it exists. So the final note matters most.
Suppose workup rules out stroke and the patient has no symptoms left. Then Z03.89 may fit. Always follow the provider’s final statement. Never build an icd 10 code for stroke from a doubtful note.
History of Stroke ICD 10: Z86.73
History of stroke ICD 10 coding uses Z86.73. Its full title is “Personal history of transient ischemic attack (TIA), and cerebral infarction without residual deficits.” The code applies to an old stroke with no lasting deficits.
Coders also search history of cva icd 10. The answer is the same. The inclusion terms even list “personal history of stroke NOS without residual deficits.”
Z86.73 has an Excludes1 note for I69 codes. So you cannot report both on one claim. Use Z86.73 when the patient has fully recovered. Use I69 when deficits remain.
What Is the ICD-10 Code for Post Stroke?
“Post stroke” has no single code. Coders use category I69, sequelae of cerebrovascular disease. The code shows what remains after the acute event. The fifth character group depends on the original stroke type.
| Code | Original Event |
| I69.0- | Subarachnoid hemorrhage |
| I69.1- | Intracerebral hemorrhage |
| I69.2- | Other nontraumatic intracranial hemorrhage |
| I69.3- | Cerebral infarction |
| I69.4- | Stroke not specified as hemorrhage or infarction |
Stroke With Residual Deficits ICD 10 Codes
Stroke with residual deficits ICD 10 coding names each deficit. The I69.3 family shows the pattern.
| Code | Deficit After Cerebral Infarction |
| I69.30 | Unspecified sequelae |
| I69.31- | Cognitive deficits |
| I69.32- | Speech and language deficits, such as aphasia (I69.320) |
| I69.33- | Monoplegia of upper limb |
| I69.34- | Monoplegia of lower limb |
| I69.35- | Hemiplegia and hemiparesis |
| I69.36 | Other paralytic syndrome |
| I69.39- | Other sequelae, such as dysphagia (I69.391) |
The note must link the deficit to the old stroke. Linking words like “due to” or “secondary to” help. Without that link, payers may question the code.
Here is a real example. A patient visits three months after a stroke. The provider writes, “Dysphagia due to prior cerebral infarction.” The coder reports I69.391. The coder also adds a code from R13.1- to show the type of dysphagia.
What Is the ICD-10 Code for Stroke Recrudescence?
Stroke recrudescence means old deficits return briefly without a new stroke. Infection, low blood pressure, or low sodium often trigger it. Imaging shows no new damage. Symptoms usually clear within a day.
The index directs coders to sequela codes. AHA Coding Clinic also supports sequela codes for deficits documented as recrudescence. So the code comes from I69, not I63. The coder should also report the trigger when the provider documents it.
For example, a patient with past aphasia develops pneumonia. Her speech problems return, and MRI shows no new infarct. The provider documents recrudescence of prior stroke deficits. The coder reports I69.320 for the aphasia, plus a pneumonia code.
However, documentation must be clear. If the note leaves doubt about a new stroke, query the provider. A wrong guess can turn a minor stay into a major audit risk.
How to Choose the Right ICD 10 Code for Stroke: Step by Step
A fixed process prevents most errors. Follow these steps for each chart.
- Read the diagnosis statement. Look for stroke type, cause, and location.
- Confirm the timing. Decide whether the stroke is acute, old, or ongoing.
- Pick the code family. Use I60 to I63 for acute, Z86.73 for history, and I69 for sequelae.
- Add specificity. Include the artery, side, or deficit when documented.
- Check Excludes notes. Z86.73 and I69 never appear together.
- Verify the code. Confirm it is billable for the date of service.
- Link the code to the service. Match the diagnosis to the visit or procedure.
This process keeps every icd 10 code for stroke tied to the chart.
Where Can I Find a Reliable Database for Stroke ICD 10 Codes?
Always verify codes against official sources. Third-party lists sometimes lag behind updates. These sources stay reliable:
- CDC and NCHS: They publish the ICD-10-CM files and official guidelines.
- CMS: It posts annual code tables and edit updates.
- AHA Coding Clinic: It gives official advice on tricky stroke cases.
- AAPC and AMA: They offer coding references and training.
- Encoder software: It searches the index and checks code edits.
New code sets take effect each October. Today is October 28, 2026, so the fiscal year 2027 set is active. Use these sources to verify any icd 10 code for stroke before you bill.
Understanding Billing for Stroke Diagnosis Codes
A correct icd 10 code for stroke does not guarantee payment. The claim also needs a matching service, clear notes, and active coverage. So billing teams follow a set process.
- Verify coverage. Confirm the plan is active, especially for rehab and home health after discharge.
- Capture the stroke type. Record ischemic or hemorrhagic, plus cause and location.
- Assign the diagnosis. Pick the code that matches the care stage.
- Match the service. Link inpatient, rehab, or office care to the right diagnosis.
- Submit and track. Watch for edits, rejections, and denials.
Stage matters more than most teams think. Acute codes belong to the active episode of care. After that stage, claims shift to Z86.73 or I69 codes. Therefore, a rehab or follow-up claim with an acute code often raises red flags.
Key Optimization Methods
These methods protect every code you report on a stroke claim.
| Method | What It Means | Benefit |
| Document specifics | Record stroke type, artery, side, and cause | Fewer queries and denials |
| Link deficits to the stroke | Use “due to” language in notes | Valid I69 reporting |
| Separate stages of care | Use acute, history, and sequela codes correctly | Cleaner claims |
| Query unclear notes | Ask the provider before coding | Lower audit risk |
| Audit monthly | Review a sample of stroke claims | Spot patterns early |
Best Tools and Practices
| Tool or Practice | Purpose | Tip |
| Encoder software | Searches the index and validates codes | Update it every October |
| Claim scrubber | Flags mismatched stage and service | Review edits daily |
| EHR stroke templates | Prompt for type, artery, side, and deficits | Keep fields short |
| Virtual Medical Scribe support | Captures stroke details during the visit | Review notes for accuracy |
| Coder education | Keeps staff current on guidelines | Hold short monthly sessions |
Future Trends
| Trend | What to Expect | Action |
| AI-assisted coding | Software suggests codes from notes | Keep human review in place |
| Telestroke growth | More remote stroke evaluations | Confirm payer telehealth rules |
| Tighter risk adjustment audits | More review of sequela codes | Document deficit links clearly |
| Real-time eligibility tools | Instant benefit checks | Adopt them early |
| Stroke registry reporting | More quality data demands | Track severity and outcomes |
Common Mistakes
| Mistake | Why It Hurts | Fix |
| Using I63.9 when detail exists | Claim looks vague | Read the full note |
| Using an acute code at follow-up | Payer flags the stage | Switch to Z86.73 or I69 |
| Reporting Z86.73 with I69 | Violates an Excludes1 note | Pick one based on deficits |
| Coding “rule out stroke” as stroke | Reports an uncertain diagnosis | Code symptoms in outpatient care |
| Skipping the deficit link | Weakens sequela support | Add “due to” language |
| Coding stroke recrudescence as a new stroke | Overstates the event | Use I69 codes and query if unclear |
Other Code Families Teams Often Review
ICD 10 code for stroke is not the only diagnosis that needs careful notes. For example, skin tag ICD 10 coding uses L91.8 and follows the index by body site. Anemia in pregnancy ICD 10 coding belongs to the pregnancy chapter, so it uses different rules than general anemia. The ICD 10 Code for Vit D Deficiency is E55.9 when the note gives no further detail. Each one rewards the same habit: read the note first, then code.
How USA RCM Solutions Supports Stroke and Neurology Billing
Stroke claims need accurate codes and steady follow-up. USA RCM Solutions helps practices and facilities handle both, so each icd 10 code for stroke matches the chart.
The team offers Medical Billing & Coding Services for acute and follow-up claims.
Practices also use its Medical Credentialing Services to join payer networks faster.
Cash flow improves with its Accounts Receivable Services.
When claims fail, Denial Management Services helps recover lost revenue.
A Virtual Medical Scribe can capture stroke details so notes support the right code.
Finally, Healthcare Marketing Services help practices reach new patients.
Conclusion
The ICD 10 code for stroke starts with the stroke type. I63.9 covers unspecified ischemic stroke, while I60 to I62 cover bleeding. Z86.73 handles an old stroke with no deficits, and I69 handles lasting deficits. Stroke recrudescence also follows the I69 path.
Accurate notes make every choice easier. Document the type, cause, artery, side, and deficit links. Then match the diagnosis to the correct stage of care.
Finally, verify each icd 10 code for stroke against official CDC and CMS sources each October. With clear documentation, your stroke claims can move through payers with fewer delays.
FAQs
How do I report the NIHSS score with a stroke code?
The NIHSS is a stroke severity score. Coders report it with R29.7- codes, and the last two digits match the score. For example, R29.712 means a score of 12. Pair it with the acute I63 code, and report at least the first documented score. Clinicians other than the provider may document the score.
Which side counts as dominant when coding hemiplegia after a stroke?
The note should state which side is dominant. If it does not, ICD-10-CM sets defaults. A right-sided deficit defaults to dominant, and a left-sided deficit defaults to non-dominant. For an ambidextrous patient, the default is dominant. So coders should check the note before they accept a default.
Can I use an acute stroke code at an office follow-up visit?
Generally, no. Acute codes belong to the active episode of care. After the patient leaves acute care, the visit usually uses Z86.73 or an I69 code. The provider’s note should show whether deficits remain. Therefore, an office visit for an old stroke rarely supports I63.
What code shows that a patient received tPA at another hospital?
Use Z92.82 for this situation. It means status post administration of tPA in a different facility within the last 24 hours before admission. Report it with the acute I63 code at the receiving facility. The record should show where and when the patient received the drug. This detail helps explain the treatment timeline.